Chronic pelvic pain can be difficult to diagnose because the place where someone feels pain does not always reveal where that pain originates. It is generally defined as persistent or recurrent pain in the pelvic region lasting for several months. Definitions differ somewhat among medical organizations, but many use a duration of at least three to six months.
The pelvis contains reproductive organs, the bladder, bowel, muscles, connective tissues and nerves packed in within a relatively small region. Problems involving any of these structures can produce pelvic pain, and symptoms from different organ systems frequently overlap.
For patients, that complexity can mean moving between doctors, physical therapists and specialists while searching for an explanation. For clinicians, it creates a different problem: pelvic pain is a symptom, not a single disease, and finding one possible source does not necessarily explain everything a patient is experiencing.
A World Health Organization (WHO) systematic review by Latthe et al. identified 178 studies involving nearly 460,000 participants with different types of pelvic pain. Among higher-quality studies with representative populations, prevalence estimates ranged from:
- 2.1% to 24% for noncyclical pelvic pain
- 8% to 21.8% for dyspareunia
- 6.8% to 81% for dysmenorrhea
This wide range does not necessarily mean that pelvic pain was dramatically more common in some countries than others. Latthe et al. found that differences in study quality and methodology contributed to the variation in reported rates.
The evidence was also unevenly distributed across the world. Studies reporting prevalence data were available from about half of developed countries, compared with only 20% of less-developed countries and 2.2% of the least-developed countries.
What causes pelvic pain?
Pelvic pain may be associated with:
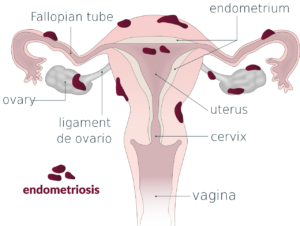
- Gynecological conditions, such as endometriosis and adenomyosis
- Urinary disorders, such as interstitial cystitis or painful bladder syndrome
- Gastrointestinal conditions, such as irritable bowel syndrome (IBS)
- Musculoskeletal problems involving the pelvic floor
- Neurological conditions affecting pelvic nerves
Sometimes several of these exist at the same time. Researchers often use the term “chronic overlapping pain conditions,” or COPCs, to describe disorders that commonly occur together.
For example, a 2024 study published in Women’s Health examined 525 women reporting chronic pelvic-abdominal pain. About one-quarter reported endometriosis. Those women reported greater pelvic pain severity, interference and overall pain impact than women without endometriosis. They were also more likely to report multiple pain conditions, where 25% of women with endometriosis reported three or more overlapping pain conditions, compared with 12% of women without endometriosis. However, endometriosis did not fully account for the difference.
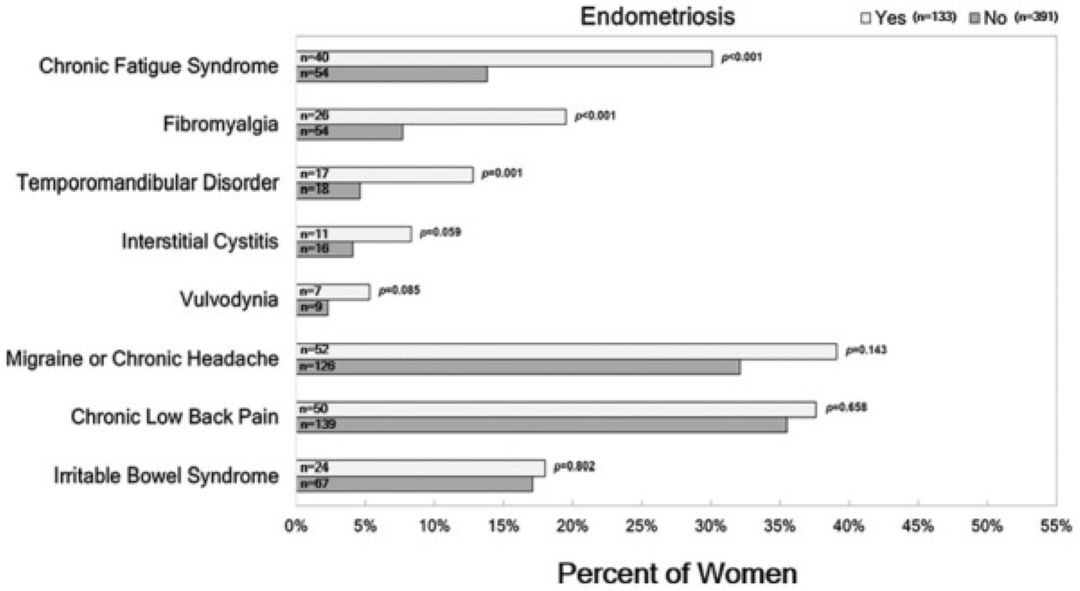
Across the study, having more overlapping pain conditions was associated with greater pain severity, interference and impact regardless of whether a participant reported endometriosis.
That pattern is also reflected in the broader chronic pain literature. A 2026 review by d’Incau et al. found that people living with multiple chronic overlapping pain conditions tend to experience a disproportionate burden, including greater pain, functional limitations, disability, sleep problems and poorer quality of life. The review several conditions that commonly intersect with pelvic pain, such as endometriosis, IBS, interstitial cystitis/bladder pain syndrome and vulvodynia.
The broader science of pain
Pelvic pain is often difficult to locate because internal organs do not convey pain in the same way as the skin or musculoskeletal tissues.
Visceral pain is often diffused and poorly localized. A 2010 systematic review by Ustinova et al. discovered that different pelvic organs also share portions of their sensory pathways.
The bladder, bowel region, and uterus send sensory information through several of the same major nerve pathways before those signals reach the spinal cord and brain. Irritation of one pelvic organ may alter sensory processing associated with another.
Ustinova et al mentioned that in experimental animal research, irritation of the colon has been shown to increase the sensitivity of nerves serving the bladder. They proposed that shared peripheral nerves, spinal reflexes and changes in central processing could all contribute to this pelvic-organ “cross-talk,” also known as cross-sensitization.
One review reported that 40% to 60% of people with IBS also had symptoms consistent with interstitial cystitis or painful bladder syndrome, while as many as 52% of people with bladder pain syndrome had symptoms consistent with IBS.
Cross-sensitization is not a proven explanation for every case of chronic pelvic pain, and much of the mechanistic evidence comes from animal models.it provides one possible explanation for why apparently separate pelvic organs can become involved in the same pain experience.
A related concept is central sensitization, which refers how the central nervous system changes and responds to sensory information, sometimes referring to increased sensitivity to painful or typical non-painful stimuli.
Research on endometriosis suggests that the extent of visible disease doesn’t always closely match the pain severity. In a 2024 cross-sectional survey, Bartley et al. also pointed out that heightened pain sensitivity both in the pelvis and elsewhere in the body among some people with endometriosis. That may help explain why treating an identifiable lesion does not always eliminate chronic pain.
A research problem, too
The WHO systematic review described major gaps in reliable prevalence data, particularly outside wealthier countries. Even among the available studies, differences in methodology were large enough that the researchers declined to combine prevalence estimates into one number.
Bartley et al. noted in their 2024 study that multiple coexisting pain conditions have received relatively little attention in endometriosis, despite evidence linking them with poorer functioning and lower treatment effectiveness.
The racial-disparities literature contains similar holes. A 2023 review of fibroids and endometriosis noted that benign gynecological conditions have been relatively understudied compared with areas, such as pregnancy and cancer. Whether those evidence gaps correspond to a measurable historical or current funding disparity, however, requires a separate analysis of research investment.
Taken together, these studies point to substantial gaps in the evidence on chronic pelvic pain.
“Why doesn’t my doctor believe me?”
Pain is inherently subjective. There is no blood test or scan that directly measures how intensely another person hurts. Clinicians therefore depend heavily on what patients tell them. That leaves room for bias.
A 2024 study by Guzikevits et al. published in Proceedings of the National Academy of Sciences examined pain-management decisions using emergency department data from the U.S. and Israel involving 21,851 patients.
Women were less likely than men to receive pain medication for similar complaints, even after researchers adjusted for patients’ reported pain scores and numerous other patient, physician and emergency department variables.
In one dataset of 17,576 emergency-department visits, 38% of female patients received an analgesic prescription compared with 47% of male patients. The disparity appeared across mild, moderate and severe pain categories and among both male and female physicians.
In the first study, female patients were also less likely to have their pain scores recorded and spent longer in the emergency department. In a third study within the same paper, Guzikevits et al. conducted a controlled experiment in which healthcare providers evaluated identical clinical scenarios involving a male or female patient. Participants rated the female patient’s pain as less intense than the male patient’s pain.
These findings were not specific to pelvic pain, so they cannot establish that every woman with pelvic pain encountered the same bias.
Race and access to care can introduce additional disparities. A 2023 systematic review examining uterine fibroids and endometriosis found that Black women with these conditions experienced worse clinical and surgical outcomes than white women. The authors pointed to differences in healthcare access, availability of highly skilled gynecologic surgeons, and bias and discrimination within the healthcare system as potential contributors. Problems that may affect gynecological care includes delayed diagnosis and treatment, unequal access, dismissal, and misattribution.
A separate U.S. scoping review of endometriosis found that white women were more likely to receive minimally invasive procedures than non-White women, while Black women experienced higher perioperative complication rates and mortality. However, only four studies met the review’s inclusion criteria, illustrating how limited the evidence base remains.
There is also a clinician’s side to the problem. Tests can be inconclusive because symptoms can originate from several organ systems. Therefore, not finding an abnormality on the first scan doesn’t mean a clinician has ignored something obvious or a patient’s pain is not real.
A 2024 qualitative study interviewed 10 people in the Netherlands with chronic pelvic pain who underwent several evaluations with different clinicians. The consultation did not substantially improve the participants’ pain, yet patients still described value in receiving a comprehensive assessment and in feeling that healthcare professionals recognized their complaints.
Treatment rarely means one type
When several factors are contributing to chronic pelvic pain or the source remains uncertain, clinicians may offer several types of treatments. This can involve gynecology, urology, pain medicine, psychology and pelvic-floor physical therapy.
Pelvic-floor physical therapy can address pelvic-floor hypertonicity, a condition in which the pelvic-floor muscles remain overly tense or do not relax normally. Hypertonicity can occur with urinary, gynecological, gastrointestinal and sexual symptoms as well as chronic pelvic pain. Physical therapy may include education, relaxation and awareness training, exercises, manual treatment.
A 2022 systematic review identified 10 studies of pelvic-floor physical therapy for pelvic-floor hypertonicity, including four randomized controlled trials.
Three of the four trials reported positive effects of physical therapy compared with controls on most assessed outcomes. Prospective studies in the review also reported improvements, but the authors wrote much of the evidence to be low or moderate quality because of small samples, lack of comparison groups and non-standardized treatments.
More recent evidence has examined physical therapy specifically for endometriosis-associated pain.
A 2026 systematic review and meta-analysis included seven studies that found that physical therapy reduced pain scores by nearly two points more than other treatments on a standard 10-point pain scale.
The researchers called for larger studies and longer follow-up, particularly because different physical-therapy techniques have been studied and it remains unclear which approaches work best for which patients.
Medication and surgery may also be appropriate depending on the underlying condition. The problem is that removing or suppressing one peripheral source of pain may not address every mechanism maintaining chronic symptoms, particularly when overlapping conditions or sensitization are involved.
How is pelvic pain diagnosed?
The process to diagnose pelvic pain starts with you giving your healthcare practitioner a thorough health history. Describing your pain and symptoms is the first step in getting to what’s causing your problem.
After your health history is complete, the physician will perform a physical exam where they examine your abdomen and pelvis as well as the organs, muscles, and tissues in your pelvic region for pain or tenderness that might lead to a diagnosis.
Based on your exam, additional testing may be indicated. Your physician might send you for blood work, urinalysis, or more advanced testing, such as pelvic ultrasound or laparoscopy, MRI, cystoscopy (instrumented-assisted view of the bladder), or a colonoscopy (instrument-assisted view of the bowel).
It’s important to note that all of the body’s organs and systems interact with one another to create homeostasis so infection or dysfunction in one area can lead to seemingly unrelated problems in another area.
Blood and urine tests
Laboratory testing can be used to detect elevated white blood cell counts, pregnancy, sexually transmitted infection (STI), or a urinary tract infection (UTI).
CT scan
CT scans can help your clinician visualize masses or tumors that may be cancerous as well as fractures, intra-abdominal bleeding, obstructions, and appendicitis. They can also detect signs of pelvic inflammatory disease (PID) via thickened uterosacral ligaments and swollen lymph nodes.
Ultrasound
Ultrasound is a helpful tool for looking at the pelvic organs and can be performed internally (transvaginal) or externally (transabdominal). While transvaginal ultrasound may be uncomfortable, the procedure should not be painful. Some of the conditions that ultrasound can help healthcare providers visualize are abnormalities in the uterus, tumors, PID, bleeding, and ectopic pregnancy.
Laparoscopy
Laparoscopy is a diagnostic procedure that is used to evaluate your abdominal organs. The laparoscope is a thin, lighted tube that has a video camera; the tube is inserted into a small incision in your belly and recovery is much faster than with traditional surgery. Laparoscopy allows your doctor to check for tumors, bleeding, infection, blockages, unexplained pain, and other conditions.
Hysteroscopy
Hysteroscopy is performed using a flexible, thin, lighted tube called a hysteroscope. The hysteroscope is inserted through your vagina and can be used to take a biopsy (tissue sample), remove polyps or fibroid tumors, or to prevent bleeding through the use of electric current, freezing, heat, or chemical to destroy problematic tissue.
STD tests
Because STIs are associated with PID, you may need a test to determine the presence of an infection. The most common infections associated with PID are chlamydia and gonorrhea. Bpth infections can be detected by the same test which can be performed at home or in a lab through a urine sample.
Pregnancy tests
There are two types of pregnancy tests- blood and urine. The urine tests are easy to find at your local pharmacy or drugstore. Blood tests are more accurate and can detect pregnancy sooner but need to be performed in your doctor’s office.
Palpatory
To find the source of your pelvic pain your doctor may press on specific areas in your abdomen to elicit pain in a particular organ in an effort to direct their diagnosis and treatment. They may also perform an internal exam to determine if the muscles of the are in spasm or if they are able to contract and relax normally.
Can I treat pelvic pain at home?
The suggested remedies for pelvic pain can vary based on your diagnosis. Some tried and true options are over-the-counter pain relievers, a warm bath or heating pad, meditation, massage, CBD oil, and rest.
Exercise may seem like the last thing you want to do when you are in pain, but the increase in blood flow coupled with the release of endorphins (a chemical response to exercise that makes you feel good) can provide an at-home pain relief option.
Dr. Alexandra “Alex” Hill, a physical therapist at UFHealth Jacksonville and the owner of OncoPelvic PT, LLC, suggests these home remedies and more. “The main thing to work on with pelvic pain is calming down the nervous system,” Hill said.
She encourages diaphragmatic breathing, which is the practice of taking slow, deep breaths in through the nose that fill your abdomen and chest and then breathing out slowly through your mouth. Diaphragmatic breathing can be done throughout the day and with any pain flares. Hill also recommends doing a “body check” throughout the day. To do this, scan your body from head to toe and learn which groups of muscles tend to hold tension.
“By learning to check in with your body and understanding how it responds to stress, you will better be able to relax your muscles,” she said. “Common muscle groups that tend to hold stress when pelvic pain is present include the jaw, abdomen, glutes, and pelvic floor.”
Most information sources will use the term exercises, but Hill really describes this more as gentle, daily movement. She advises that finding ways to get outside and get moving can be particularly helpful.
“This can include walking, yoga, or gardening; anything that gets you moving!” she said.
When should I see my doctor for pelvic pain?
As with most conditions, not all pelvic pain is created equal. Deciding when to see treatment can be a difficult decision to make. You should seek immediate treatment from the nearest emergency room if you have sudden pain that is sharp or severe, are or were recently pregnant, have bloody urine or stool, or can’t stand up because of the pain.
Less severe symptoms should still lead you to make an appointment with your physician or physical therapist to get relief. You’ll know it’s time to seek help if your pain lasts more than a few weeks, worsens during sexual intercourse, or affects your activities of daily living. Pain that doesn’t improve, comes and goes, or increases in frequency or intensity should be discussed with a healthcare practitioner.
“If pain is felt in the pelvic region (including the abdominal, vaginal, and/or rectal areas), an individual will benefit greatly from the assistance of a pelvic floor physical therapist as soon as possible,” said Dr. Lindsay Fader, a physical therapist and the founder and president of The Pelvic Advantage, a women’s health agency focused on the functional improvement in women’s bodies before, during, and after pregnancy and surgery.
“Most of the women I treat have hypertonic pelvic floor muscles and this increased tension is a key component of their pain,” Fader said. “It is important to be evaluated by a pelvic floor physical therapist to become aware of the state of the pelvic floor muscles and what each woman’s specific body needs to improve pelvic health and function without pain.”
Is there progress?
Many clinicians and researchers are rethinking about pelvic pain. One is the growing recognition that chronic pelvic pain may cross the boundaries between traditional medical specialties. Several clinical guidelines now recommend multidisciplinary care. Rather than moving patients from one specialist to another in search of a single explanation, future chronic pelvic pain care may increasingly rely on earlier multidisciplinary assessment.
At Radboud University Medical Center in Nijmegen, the Netherlands, for example, patients with chronic pelvic pain can be assessed by a multidisciplinary team that includes gynecologists, pain specialists, urologists, pelvic-floor physiotherapists and psychologists, according to a 2025 qualitative study.
The Bartley et al. study measured not only pain intensity but also pain interference. Using the Brief Pain Inventory, the researchers assessed how pelvic pain affected general activity, mood, walking, work or household activities, relationships, sleep and enjoyment of life. These measures capture aspects of the pain experience that an intensity score alone cannot fully describe.
Pelvic pain resources
For clinicians
Entropy Physiotherapy and Wellness, Chicago, Illinois
Evidence in Motion, San Antonio, Texas
Beyond the Kegel, Institute for Pelvic Health, Boston, Massachusetts
The Enigma of Female Pelvic Pain
Pain Science for the Chronic Pelvic Pain Population
For patients
Conquering Pelvic Pain: Fitness & Education to Empower Women, Princeton, New Jersey
International Pelvic Pain Society

Penny Goldberg, DPT, ATC
Penny Goldberg, DPT, ATC earned her doctorate in Physical Therapy from the University of Saint Augustine and completed a credentialed sports residency at the University of Florida. She is a Board Certified Clinical Specialist in Sports Physical Therapy.
Penny holds a B.S. in Kinesiology and a M.A. in Physical Education from San Diego State University. She has served as an Athletic Trainer at USD, CSUN, and Butler University.
She has presented on Kinesiophobia and differential diagnosis in complicated cases. Penny has published on returning to sports after ACL reconstruction and fear of movement and re-injury.
Outside of the clinic, Penny enjoys traveling, good cooking with great wine, concerts, working out and playing with her dogs.

Dezare Lozano
Dezare graduated from of San Diego State University in 2025 where she earned a degree in journalism with a minor in English. During her studies, she emphasized news writing and gained experience reporting and producing news stories.
Dezare is focused on expanding her skills across additional areas of journalism, including working in a newsroom at a large newspaper organization and traveling to capture compelling photojournalism. She also aspires to become a journalism professor in the future.
In her free time, Dezare enjoys sharpening her camera and writing skills. She also likes cooking, animating, and working on creative writing side projects.